
States Pour $200M Into Rural Physician Pipelines
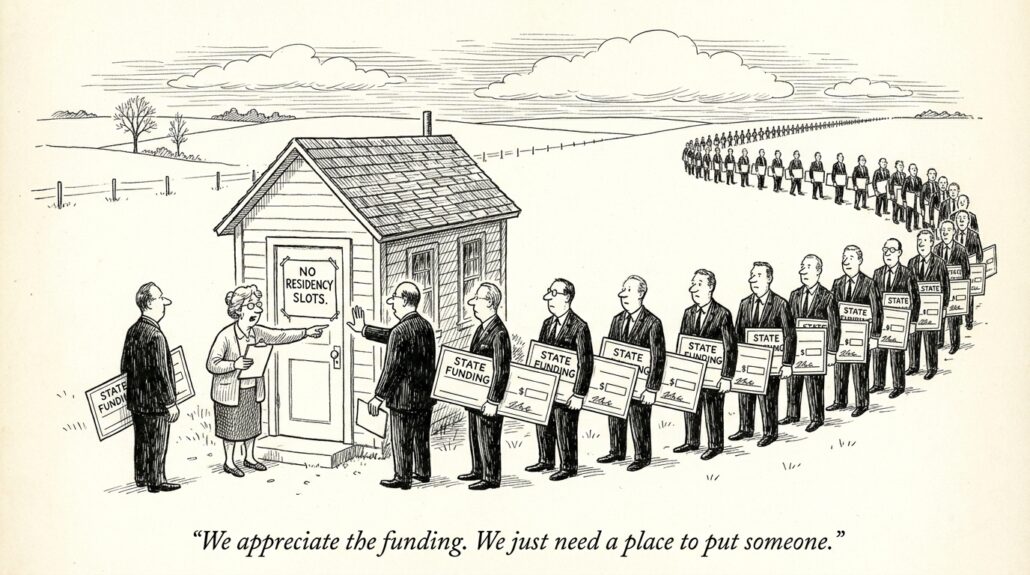
State investments exceeding $200 million are reshaping rural physician workforce strategy, shifting from recruitment bonuses to embedded training infrastructure. New research shows rural residency training increases subsequent rural practice by 42%, explaining why states from Alabama to Arizona are funding medical education pipelines rather than competing for physicians trained elsewhere.
Signs You’re in a Toxic Residency Program — and the Options Residents Actually Have
An open letter to a program director alleging falsified educational hours, denied breaks, racial favoritism, and repeated ignored complaints. A resident facing possible job loss over a certification case list that the institution’s own EHR tooling won’t produce. A PGY-1 with no consistent onboarding, learning expectations only through repeated, unwritten mistakes. A resident with severe […]
FDA AI Testing Rules May Reshape Physician Authority

The FDA’s proposal to test generative AI medical devices against physician competency standards creates a regulatory framework with direct implications for physician compensation models. As health systems gain defensible benchmarks for comparing AI and physician performance, contract structures and specialty valuations face restructuring pressure that will reshape employment negotiations for years.
Teaching While You Still Feel Like a Learner: How New Senior Residents Build Real Confidence
A new PGY-2, anxious about teaching interns and students, describes their own knowledge base as “superficial.” Another resident describes feeling like “a nobody” next to a high-performing peer, questioning whether they’ve earned the right to be called a doctor. An ID fellow openly names feeling behind relative to their new environment. Different training levels, same […]
Retention Ownership Gaps Fuel Physician Unionization Wave

Only 39% of healthcare organizations have formal retention strategies, yet 47% of physicians now consider unionization viable—with the UC system’s 10,000-physician campaign and Banner Health’s September vote marking inflection points where compensation-only approaches collide with demands for operational voice and clinical autonomy.
How to Get Up to Speed Fast on a New Service: A Resident’s System for Learning Guidelines, Workflows, and Unwritten Rules
An ID fellow two months into a move from community residency to an academic center, drowning in consult volume and guideline lookups. A PGY-1 describing service switching as harder than the hours themselves — “six operating manuals with no tabs.” A resident hunting for a nuclear medicine atlas, trying to build knowledge from zero. Different […]
PMHNP Demand Outpaces Staffing Market Recovery Rates

Healthcare staffing’s return to modest growth masks sharp specialty divergence, with PMHNPs accelerating faster than aggregate figures suggest while physician retention efforts remain largely rhetorical. Telehealth-enabled psychiatric roles in full practice authority states now set compensation benchmarks that pressure traditional positions, creating strategic opportunities for APPs who understand regulatory geography.
The Midlevel Expansion Problem: What Residents Need to Know About NP and PA Scope Creep Before Entering the Job Market

NP and PA scope expansion is reshaping parts of the physician job market—but not uniformly. Primary care and lower-acuity settings face the most direct competition, while procedural and complex subspecialties remain more insulated. Understanding where the pressure is concentrated, and positioning your career accordingly, is essential for residents entering a workforce where midlevel competition is a structural reality.
Retention Ownership Gap Drives Hidden Turnover Risk

New data reveals that only 39% of healthcare organizations have formal physician retention strategies—and most cannot identify who owns retention efforts. With excessive work hours now directly linked to quit intentions and mid-career attrition accelerating, the absence of designated retention accountability creates hidden turnover costs that surface only in recruiting metrics.
Why Finishing Residency Doesn’t Fix You: The Burnout, Identity Loss, and Recovery That Comes After Training

Finishing residency doesn’t automatically restore wellbeing—survival habits formed during training become entrenched, identity tied to being a trainee dissolves, and anticipated relief often arrives as emptiness. Recovery requires intentional intervention: rebuilding physical health, reconnecting with pre-medicine identity, and recognizing when post-residency malaise crosses into clinical depression.